


You can explain your clinical plan in five minutes. But explaining it to an SBA lender is a different thing entirely. A lender wants to see numbers most physicians have never had to think about before:
- whether the practice can comfortably repay the loan
- how long insurance payment takes to arrive
- how many patient visits it takes to cover costs
- where the startup funding will exactly go
These questions rarely come up in clinical training, and not knowing them is where a lot of strong applications stall.
That’s why I’ve created this sample plan for Northbrook Family Medicine, a fictional solo practice in Haywood Springs, North Carolina. It shows how those clinical and financial decisions come together in a lender-ready business plan.
Use it as a reference as you build your own plan.
Executive Summary
Northbrook Family Medicine, PLLC is a physician-owned primary care practice opening in February 2027 in Haywood Springs, North Carolina, a suburb in the Raleigh-Durham area.
The practice will be owned and run by Dr. Rachel Donovan, MD, a board-certified family physician with 11 years of experience. Northbrook will provide:
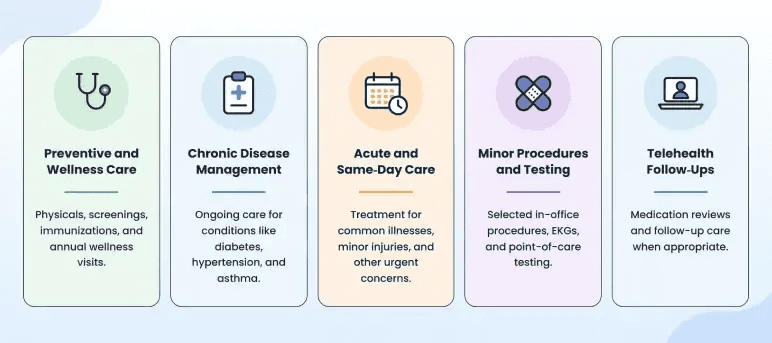
It will mainly serve insured families and working adults, and will also see Medicare patients and a limited share of Medicaid patients.
How Northbrook Is Different
The practice is based on continuity and access. Dr. Donovan sees the majority of patients, and part of each day is devoted to urgent care.
This enables patients to receive routine and urgent primary care in the same practice, which differentiates Northbrook from larger practices where it often takes longer for patients to get an appointment and they see a different clinician each time.
Team & Office
Northbrook will open with a lean team, consisting of Dr. Donovan and a medical assistant, front-desk and administrative personnel, part-time nurses as patient volumes increase, and outside billing services. The office is approximately 2000 sq ft and uses only one EHR (Electronic Health Record) and one practice-management system.
Funding Request
Northbrook needs $325,000 to open. Dr. Donovan will put in $80,000 of her own money, and the practice is seeking a $245,000 SBA 7(a) loan from Summit Community Bank.
The money will be used for leasehold improvements, medical equipment, technology, setup costs, and a big working capital reserve. This reserve is important because insurance payments do not happen instantly.
The plan assumes about 40 days from the visit to the payment, so there is a real gap between seeing a patient and receiving the cash.
Financial Outlook
Patient visits are expected to grow from 3,600 in Year 1 to 5,625 in Year 3. The forecast uses an average net collection of $135 per completed visit.
| Financial Metric | Year 1 | Year 2 | Year 3 |
| Patient visits | 3,600 | 4,500 | 5,625 |
| Revenue | $486,000 | $607,500 | $759,375 |
| Gross profit | $383,595 | $479,494 | $599,366 |
| Net income (pre-tax) | ($64,150) | $14,391 | $90,996 |
| Ending cash | $62,123 | $71,776 | $153,397 |
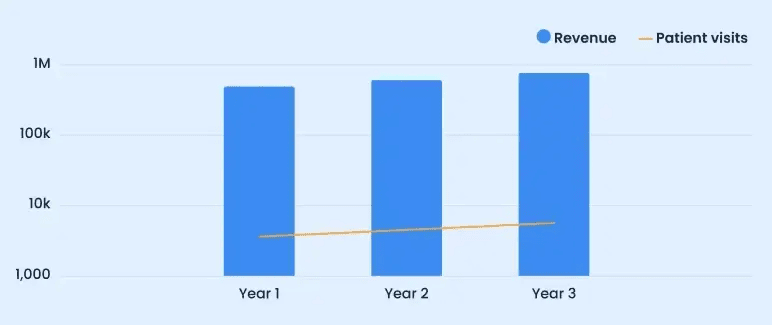
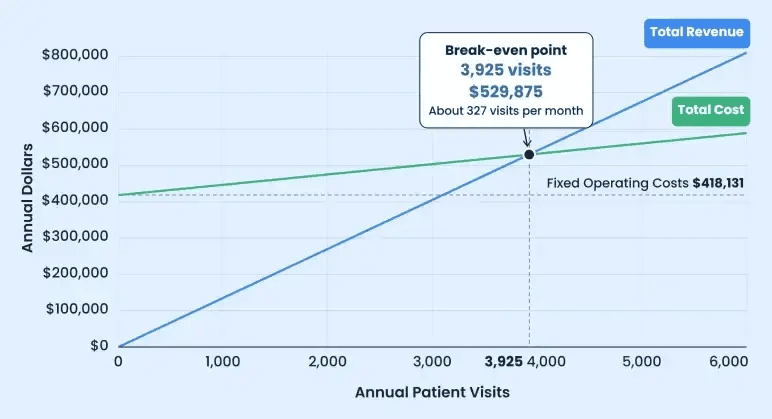
Northbrook is expected to operate at a planned loss during Year 1 while the patient panel grows. The practice needs approximately 3,925 visits per year, or about 327 visits per month, to break even. This level is expected to be reached during Year 2.
Growth Plan
By Year 3, Northbrook is expected to be operating close to the practical capacity of one full-time physician. So the practice will not automatically employ another clinician at that time.
Instead, it will look to hire a nurse practitioner or physician assistant only if patient wait times start to rise, appointment demand stays consistently high, and the provider will bring in sufficient revenue to offset the cost of their staff.
Company Overview
Business Background
Northbrook Family Medicine is the practice Dr. Rachel Donovan is building after eleven years in family medicine, the last seven in a hospital-owned group. There, visits were short, and patients were sent to whichever clinician was free, so many never saw the same doctor twice.
Dr. Donovan is leaving to run a practice built the way she thinks primary care should work. Because she already practices in the Haywood Springs area, she brings a local reputation and referral relationships that a brand-new practice usually has to build from nothing.
Practice at a Glance
| Item | Detail |
| Business | Northbrook Family Medicine, PLLC |
| Owner | Dr. Rachel Donovan, MD, board-certified family physician with 11 years of experience |
| Structure | North Carolina PLLC, 100% physician-owned |
| Location | Haywood Springs, Wake County, North Carolina |
| Facility | Leased medical office, approximately 2,000 sq. ft. |
| Business model | Insurance-based primary care focused on continuity and same-day access |
| Opening | February 2027 |
Ownership and Legal Structure
Northbrook will be a professional limited liability company (PLLC), registered in North Carolina and fully owned by Dr. Donovan, who holds an active state medical license. The PLLC keeps the practice physician-owned, as North Carolina requires, and protects her personal assets from general business liability.
Mission
Northbrook’s goal is simple: to be the practice patients stay with for years. Dr. Donovan believes that kind of long-term relationship is both better medicine and the most reliable foundation for a healthy business, and the whole practice is built to support it.
Three-Year Goals
Northbrook’s first three years follow three clear milestones:
- Year 1 is a build year. The focus is on adding patients and filling the panel, not turning a profit.
- Year 2 is the turning point. The growing panel carries the practice past break-even.
- Year 3 is a capacity decision. One physician nears full capacity, and the practice weighs a second clinician based on real demand and the numbers, not a fixed date.
Spending days structuring a business plan? Let Upmetrics handle the first draft so you can focus on the details. Get started today →
Industry and Target Market Analysis
Northbrook will operate in the Raleigh-Durham corridor of Wake County, North Carolina. It enters a large and growing sector, in one of the country’s strongest regional markets, and needs only a small share of its local area to support one physician.
Industry Overview
The U.S. physician practice market is large and growing, worth about $376 billion in 2025 and projected to reach $543 billion by 2030.
Within it, physician-owned practices are the single largest ownership segment (about 49% of the market), and practices with fewer than five physicians are the largest by size (about 36%), even as many physicians move into larger hospital-owned and corporate groups.
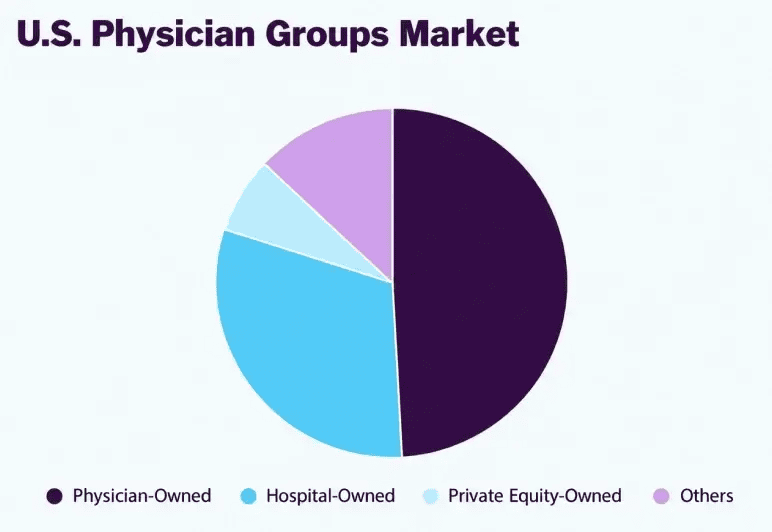
These small, independent practices compete by doing exactly what Northbrook is built for: personalized, relationship-based care that earns patient loyalty and referrals. Physician ownership remains especially common in suburban markets, and the Southeast is the largest region.
Local Demand
The market around Haywood Springs, in Wake County, is large, growing, and well insured:
- 1.26 million residents, up about 11.3% since 2020
- Median household income of about $105,768
- Only 7.2% of residents under 65 are uninsured
- 14.4% of residents are aged 65 or older
- Nearby Wake Forest grew about 21.1% between 2020 and 2025, skewing young and family-heavy
These conditions support demand from the two groups that matter most to a new practice: growing numbers of insured families and working adults who need a primary care physician, and older residents who need regular preventive and chronic-care visits.
Market Share Needed
Northbrook does not need a large share of this market to support one physician. Its primary service area, the communities within about a 15-minute drive of the office, holds an estimated 38,000 residents.
Research covering nearly 22,000 family physicians found an average panel of about 1,933 patients, though actual panel size varies by practice model, staffing, and patient needs. Using roughly 1,900 patients as a reference:
1,900 patients ÷ 38,000 residents = about 5% of the local service area
So Northbrook needs to attract and retain only a small portion of nearby residents who need ongoing primary care and fit its insurance network. This is a conservative target in a market adding thousands of residents a year.
Payer Landscape
A practice’s revenue depends not only on how many patients it sees but on who insures them, since reimbursement varies widely by payer. Northbrook plans around a deliberate, commercial-heavy mix:
| Payer | Expected share | Role in the model |
| Commercial insurance | Largest | Best reimbursement; core of insured working-age patients |
| Medicare | Second largest | Wellness and chronic-care demand among older adults |
| Medicaid | Smaller | Expands access among eligible working-age residents |
| Self-pay | Small | Copays, deductibles, and uninsured visits |
North Carolina’s Medicaid expansion, in effect since December 2023, had enrolled more than 685,000 residents by October 2025, broadening coverage among working-age adults. Northbrook will accept Medicaid while monitoring its overall mix and average collections as volume grows.
Target Patients
Northbrook will focus on three main groups of patients.
Families and working adults
They will make up the largest part of the practice. They want a doctor close to home who takes their insurance, offers easy scheduling and same-day sick visits, and stays with them over time.
Adults with ongoing chronic conditions
They matter most to how the practice runs. People with high blood pressure, diabetes, high cholesterol, or asthma come back several times a year, so their care brings steady, repeat visits instead of one-off appointments.
Medicare-age adults
They are a smaller but important group. And they need yearly wellness visits, medication reviews, chronic care, as well as help coordinating with specialists.
In choosing a primary care physician, these patients weigh insurance acceptance first, then location, then appointment availability and referrals.
Competitive Analysis
Northbrook will compete with the care options patients already use nearby: hospital-owned practices, urgent care, retail clinics, and telehealth. It does not try to win on price, since insurance sets the rates, or on size.
The comparison below shows where each option is strong and where Northbrook fits:
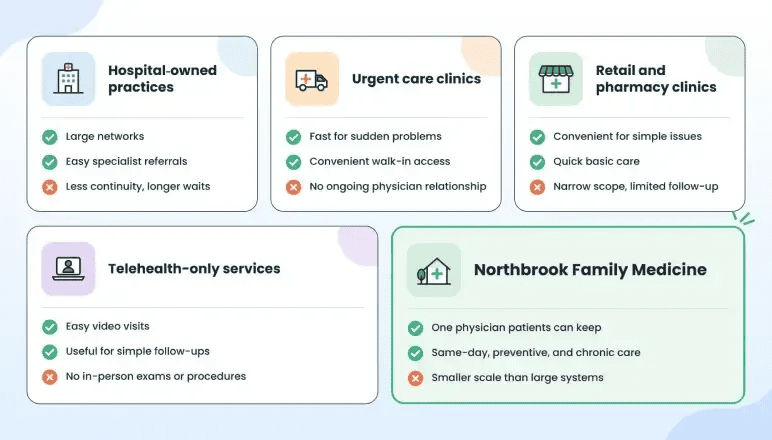
Each of these options is strong for one kind of need. The walk-in and virtual choices are convenient for a one-off problem but offer no ongoing physician relationship, while hospital-owned practices have large networks but less continuity and longer waits.
Northbrook’s Competitive Position
Northbrook’s main advantage is continuity plus access. Patients continue to visit Dr. Donovan for their routine care, and they can still get a same-day appointment when any emergencies come up.
The same office also handles their checkups, ongoing conditions, follow-ups, tests, and minor procedures over time.
This does not imply Northbrook beats all the options at everything. Urgent care or telehealth may be faster when it comes to a one-time issue, and larger health systems tend to have larger networks and more specialists.
Northbrook has been built for one narrower purpose: patients who wish to have a regular family doctor without compromising on quick access.
Services and Revenue Model
What Northbrook Offers
Northbrook will offer the full range of care a family medicine practice is expected to provide, rather than leaning on one service or one type of patient for its income. Each service line plays a different role in the business.
| Service | What it includes | Why it matters |
| Preventive and wellness | Physicals, Medicare Annual Wellness Visits, screenings, immunizations | Brings new patients in and starts long-term relationships |
| Chronic disease management | Ongoing care for diabetes, high blood pressure, and similar conditions | Creates steady, repeat visits all year; the main revenue engine |
| Acute and same-day care | Common illnesses, minor injuries, and urgent concerns in reserved daily slots | Captures demand that would otherwise go to urgent care; supports retention |
| In-office procedures and point-of-care lab testing | Small in-office procedures, EKGs, point-of-care lab tests | Adds per-visit value; keeps care in-house |
| Telehealth follow-ups | Follow-ups that do not need an in-person exam | Efficient use of physician time; improves access |
How the Practice Earns Revenue
Northbrook will be an insurance-based, fee-for-service practice using the standard evaluation and management (E/M) and procedure codes for billing insurance companies. Commercial insurance, Medicare, and Medicaid will generate the majority of revenue, along with patient copays and deductibles.
What the practice earns on a visit is the amount the insurer will pay, not the price it lists, so the forecast is built on what Northbrook actually collects per visit, not on its charges.
For planning, it uses a blended net collection of $135 per completed visit and assumes that figure is constant for the next three years. This is a conservative approach, because insurance payments are under pressure right now. CMS’s proposed 2027 Physician Fee Schedule would lower the base rate by about 1.68% from 2026, and Northbrook opens in 2027. So, the plan does not count on rate increases that may not happen.
On that basis, revenue grows from $486,000 in Year 1 to $759,375 in Year 3 as visits climb from 3,600 to 5,625. Most of that growth comes from chronic disease management, since those patients return on a regular schedule and turn one visit into a steady stream.
Northbrook will stick to core family medicine for now and add new services only when there is enough demand, the staff to deliver them, and a clear payoff for doing so.
Marketing and Patient Acquisition
Northbrook will target local, high-intent channels to help patients discover the practice when they are actively looking for a primary care physician. The key priorities will not be extensive paid advertising, but insurance network visibility, local search, professional referrals, and patient retention.
Before Opening
Before the doors open, Northbrook will complete payer credentialing with the major commercial plans used in the area, along with Medicare and selected Medicaid plans. That means patients can use their coverage from the first visit.
Alongside it, the practice will set up:
- Website with online booking
- A Google Business Profile
- Listings in insurance and physician directories
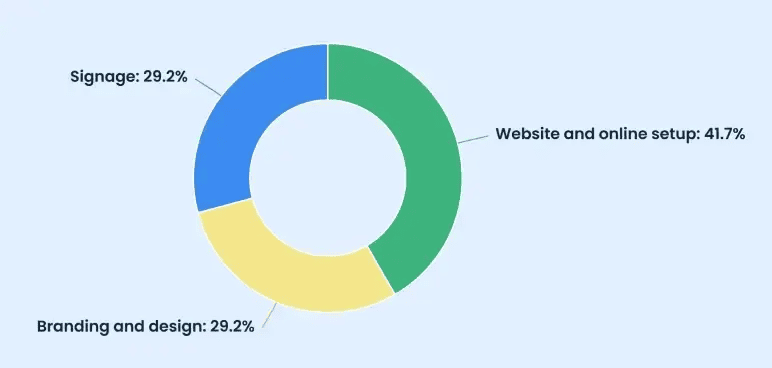
That way, local residents searching for an in-network family doctor who is accepting new patients can find it. A clear brand and office signage complete the launch.
This one-time launch work is budgeted at $12,000, separate from the yearly marketing spend.
Attracting New Patients
Once open, Northbrook will grow its patient panel (the patients who use it as their regular practice) through a few steady, low-cost channels:
- Referrals from specialists, women’s health practices, urgent care centers, pharmacies, and local employers, earned by reporting back to referring providers and keeping appointments open
- Online reviews from satisfied patients on Google and health rating sites
- Word of mouth from existing patients and their families
- Dr. Donovan’s established local relationships, which give the practice a head start
The Raleigh-Durham area adds thousands of new residents a year, many still choosing a physician, which keeps a steady flow of prospective patients. Ongoing marketing to keep these channels active is budgeted at $12,000 in Year 1, $14,000 in Year 2, and $16,000 in Year 3, growing modestly as the panel fills.
Patient Retention
Northbrook’s patients come back over time, so the practice will put real effort into keeping them, not just signing up new ones.
It will stay in touch with its patients. Give a reminder when a yearly checkup is due, a call to bring in patients who are overdue for chronic-care follow-up, easy booking and messaging through a patient portal, and same-day openings so patients come to Northbrook first when something comes up.
Marketing Performance
Northbrook will watch what actually works instead of guessing. It will keep an eye on:
- Where new patients come from
- Which channels turn into booked visits
- How often people miss appointments
- How many patients come back
Over time, it will spend more on the channels that bring in patients who stay, and less on the ones that do not.
Operations and Management
Northbrook will run as a lean, scheduled family medicine practice with one physician and a small team. The goal is to keep costs manageable in the early years while Dr. Donovan has enough support to focus on patients.
Clinical Operations
The practice will be open:
- Monday through Thursday: 8 a.m. to 5 p.m.
- Friday: 8 a.m. to 1 p.m.
A few slots stay open each day for patients who need to be seen that day. Visits will cover preventive visits, chronic-care follow-ups, new-patient appointments, sick visits, minor procedures, point-of-care testing, and telehealth follow-ups where appropriate.
The schedule starts light and fills as the panel grows, reaching about 22 visits a day once the practice is at full capacity.
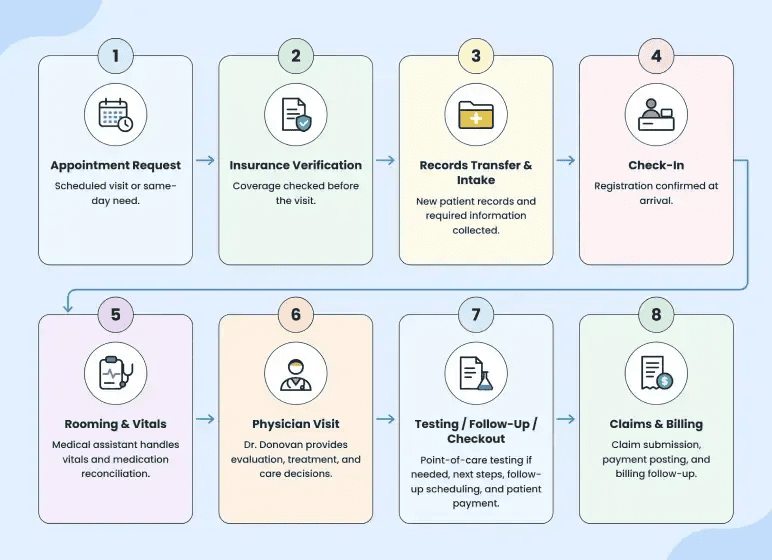
New patients will complete insurance verification and records transfer before their first visit. Clinical staff will handle rooming, vitals, medication reconciliation, basic testing, and routine follow-up tasks so Dr. Donovan can keep most of her time focused on physician-level care. The schedule will also allow time for documentation to be completed during the workday.
Since the practice opens with one physician, it will also have a coverage plan for after-hours needs, planned time off, and unexpected physician absence. The exact arrangements will be set before opening.
Staffing
Dr. Donovan will serve as Northbrook’s owner, sole physician, and clinical lead. She will be supported by a small team at launch:
(1) Medical Assistant
Helps prepare patients for visits by taking vitals, reviewing medications, assisting with basic tests, and supporting Dr. Donovan during clinical care.
(2) Front-Desk and Administrative Support
Handles appointment schedules, patient registration, insurance verifications, communication, and payment collection.
(3) Part-Time Licensed Practical Nurse (LPN)
Provides additional nursing support as patient volume increases.
(4) Outsourced Revenue-Cycle Support
Handles insurance claims, payment posting, billing follow-up, and denied claims.
Northbrook will add support staff gradually as patient volume increases rather than carrying payroll ahead of demand.
Direct clinical labor for the medical assistant and part-time nursing support will therefore increase with revenue, while Dr. Donovan’s compensation and administrative salaries are included in operating expenses.
Facility and Technology
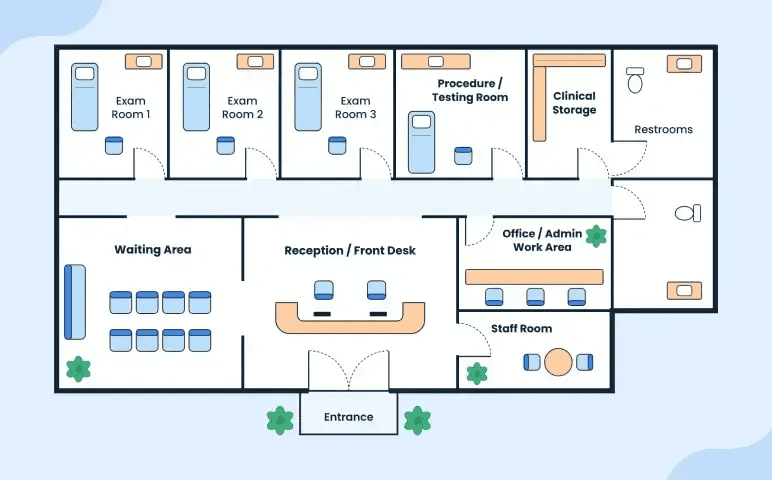
Northbrook will lease about 2,000 square feet of medical office space. The facility will include exam rooms, a reception and waiting area, administrative workspace, clinical storage, and room for point-of-care testing and minor procedures.
The practice will run on one combined EHR and practice-management system that handles charting, scheduling, e-prescribing, insurance checks, patient messages, claims, payments, and reports.
Startup equipment will include exam and diagnostic tools, an EKG, sterilization equipment, computers, networking, furniture, and the clinical supplies needed to open.
Compliance and Credentialing
Before opening, Northbrook will complete the professional, clinical, and business requirements applicable to the practice.
These include:
- North Carolina professional and business registration
- Physician licensing requirements
- Payer enrollment and credentialing
- Malpractice coverage
- HIPAA policies and safeguards
- OSHA requirements
- CLIA certification or waiver for in-office testing (if applicable)
Payer credentialing will be treated as a launch-critical task, because delays could prevent the practice from collecting insurance payments normally after patient visits.
If the practice is not properly enrolled with a patient’s health plan, a completed visit may not generate normal insurance reimbursement.
Provider Capacity and Expansion
Northbrook expects Dr. Donovan’s schedule will be close to full by Year 3, at about 5,625 visits a year. That is when the practice will look at whether it needs a second clinician.
It will bring on a nurse practitioner or physician assistant only when the appointments line up. The schedule stays busy, same-day slots fill up most days, patients start waiting longer to get in, and the expected visits are enough to cover the new provider’s compensation and support costs.
So Year 3 is a point to decide, not a fixed hiring date. Northbrook will not hire early, because a new clinician means paying a salary before that person has built up enough patients and income to pay for it. The practice will add someone only when both the patient demand and the numbers support it.
Risk Analysis
Northbrook’s forecast depends on several operating assumptions. Management will monitor the risks most capable of affecting cash flow, patient volume, or capacity.
| Risk | Potential Effect | Mitigation |
| Credentialing delays | Claims cannot be collected normally, extending the startup cash gap | Begin payer enrollment well before opening and track each payer weekly |
| Slower patient-panel growth | Lower visit volume extends the period below break-even | Maintain adequate working capital and diversify referral and discovery channels |
| Rising days in accounts receivable | Revenue is recorded, but cash arrives too slowly | Watch A/R aging, denials, claims, and payment posting closely |
| Less favorable payer mix | Average collections decline despite stable visit volume | Monitor collections and visits by payer and by common services |
| Staffing constraints | Limits daily capacity and creates workflow pressure | Add support staff gradually as volume increases |
| Physician capacity ceiling | Wait times increase, and additional demand cannot be served | Evaluate an NP or PA once utilization and financial thresholds are met |
The working-capital reserve provides Northbrook with its primary protection during the first year.
However, Northbrook will treat it as planned runway, not a reason to stop watching for problems. It will review credentialing, patient volume, schedule use, payer mix, collections per visit, and days in A/R regularly, so small variances get caught before they become cash-flow issues.
Financial Plan
Northbrook’s financial plan is built around a gradual increase in patient volume, conservative reimbursement assumptions, and enough working capital to cover the delay between providing care and receiving insurance payments.
Startup Costs
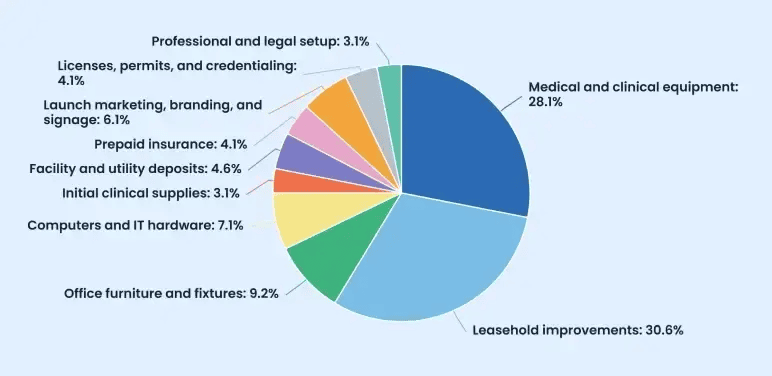
Northbrook needs $325,000 to open and operate through its first year. The largest single item is the working capital reserve, which carries the practice through the Year 1 cash gap.
| Startup cost | Amount |
| Medical and clinical equipment | $55,000 |
| Leasehold improvements | $60,000 |
| Office furniture and fixtures | $18,000 |
| Computers and IT hardware | $14,000 |
| Initial clinical supplies | $6,000 |
| Facility and utility deposits | $9,000 |
| Prepaid insurance | $8,000 |
| Launch marketing, branding, and signage | $12,000 |
| Licenses, permits, and credentialing | $8,000 |
| Professional and legal setup | $6,000 |
| Working capital reserve | $129,000 |
| Total | $325,000 |
Key Financial Assumptions
The forecast is based on the following assumptions:
| Assumption | Planning Basis |
| Average net collection per visit | $135 |
| Annual patient visits | 3,600 in Year 1; 4,500 in Year 2; 5,625 in Year 3 |
| Revenue growth | 25% annually, driven by visit volume |
| Clinical supplies | 6% of revenue |
| Direct clinical labor | 14% of revenue |
| Payroll taxes on direct labor | 7.65% |
| Accounts receivable | 40 days |
| Accounts payable | 30 days |
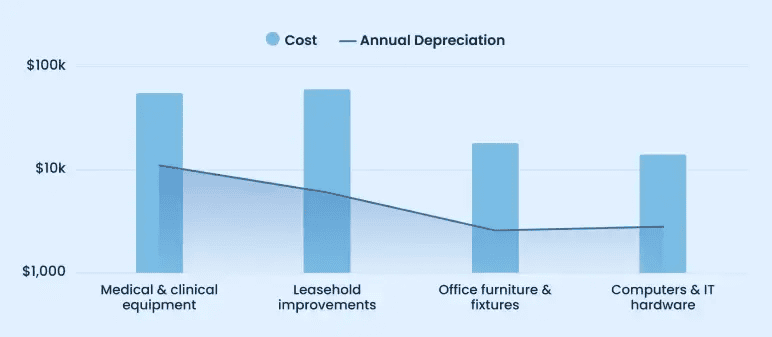
| Annual depreciation | $22,371 |
Depreciation Schedule
| Asset | Cost | Useful Life | Annual Dep. |
| Medical & clinical equipment | $55,000 | 5 years | $11,000 |
| Leasehold improvements | $60,000 | 10 years | $6,000 |
| Office furniture & fixtures | $18,000 | 7 years | $2,571 |
| Computers & IT hardware | $14,000 | 5 years | $2,800 |
| Total | $147,000 | — | $22,371 |
Projected Income Statement
| Item | Year 1 | Year 2 | Year 3 |
| Patient visits (annual) | 3,600 | 4,500 | 5,625 |
| Total Revenue | $486,000 | $607,500 | $759,375 |
| COGS | |||
| Clinical supplies (6%) | $29,160 | $36,450 | $45,563 |
| Direct clinical labor (14%) | $68,040 | $85,050 | $106,313 |
| Payroll taxes on labor | $5,205 | $6,506 | $8,133 |
| Total COGS | $102,405 | $128,006 | $160,009 |
| Gross profit | $383,595 | $479,494 | $599,366 |
| OpEx | |||
| Owner and admin salaries | $220,000 | $254,000 | $288,000 |
| Payroll taxes on salaries | $16,830 | $19,431 | $22,032 |
| Rent | $54,000 | $55,600 | $57,300 |
| Malpractice and insurance | $22,000 | $23,000 | $24,000 |
| Accounting and legal | $9,000 | $9,500 | $10,000 |
| Phone, internet, utilities | $8,400 | $8,800 | $9,200 |
| Ongoing marketing | $12,000 | $14,000 | $16,000 |
| Billing and clearinghouse fees | $7,200 | $8,400 | $9,600 |
| EHR and practice-management software | $9,600 | $10,200 | $10,800 |
| Other operating (supplies, repairs, CME, dues) | $14,100 | $15,200 | $16,300 |
| One-time launch costs | $26,000 | $0 | $0 |
| Total Operating Expenses | $399,130 | $418,131 | $463,232 |
| EBITDA | ($15,535) | $61,363 | $136,134 |
| Depreciation | $22,371 | $22,371 | $22,371 |
| EBIT | ($37,906) | $38,992 | $113,763 |
| Interest expense | $26,244 | $24,601 | $22,767 |
| Net income (pre-tax) | ($64,150) | $14,391 | $90,996 |
Projected Cash Flow Statement
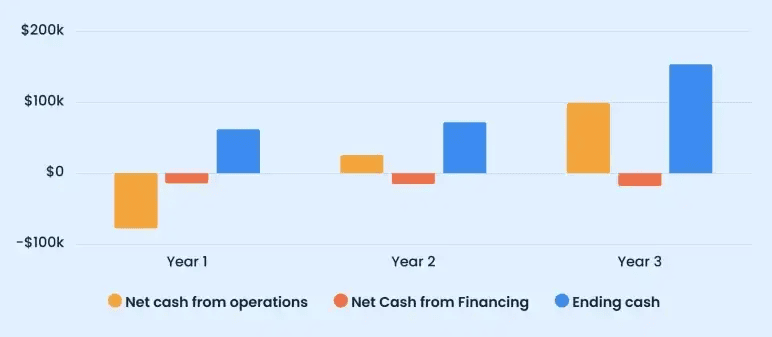
| Item | Year 1 | Year 2 | Year 3 |
| Beginning cash | $155,000 | $62,123 | $71,776 |
| Net income (pre-tax) | ($64,150) | $14,391 | $90,996 |
| Depreciation | $22,371 | $22,371 | $22,371 |
| Change in accounts receivable | ($53,260) | ($13,315) | ($16,644) |
| Change in inventory | $0 | $0 | $0 |
| Change in accounts payable | $8,417 | $2,104 | $2,630 |
| Change in prepaid expenses | $8,000 | $0 | $0 |
| Net cash from operations | ($78,622) | $25,551 | $99,353 |
| Capital expenditures | $0 | $0 | $0 |
| Net Cash from Investing | $0 | $0 | $0 |
| Loan principal repaid | ($14,255) | ($15,898) | ($17,732) |
| Net Cash from Financing | ($14,255) | ($15,898) | ($17,732) |
| Net change in cash | ($92,877) | $9,653 | $81,621 |
| Ending cash | $62,123 | $71,776 | $153,397 |
Projected Balance Sheet
| Item | Year 1 | Year 2 | Year 3 |
| Assets | |||
| Cash | $62,123 | $71,776 | $153,397 |
| Accounts receivable | $53,260 | $66,575 | $83,219 |
| Inventory | $6,000 | $6,000 | $6,000 |
| Prepaids and deposits | $9,000 | $9,000 | $9,000 |
| Net equipment and buildout | $124,629 | $102,258 | $79,887 |
| Total assets | $255,012 | $255,609 | $331,503 |
| Liabilities | |||
| Accounts payable | $8,417 | $10,521 | $13,151 |
| Term loan | $230,745 | $214,847 | $197,115 |
| Total Liabilities | $239,162 | $225,368 | $210,266 |
| Equity | |||
| Paid-in capital | $80,000 | $80,000 | $80,000 |
| Retained earnings | ($64,150) | ($49,759) | $41,237 |
| Total liabilities and equity | $255,012 | $255,609 | $331,503 |
Break-Even Analysis
| Item | Value |
| Blended revenue per visit | $135.00 |
| Clinical supplies per visit (6%) | $8.10 |
| Direct clinical labor per visit (14%) | $18.90 |
| Payroll taxes on direct labor per visit | $1.45 |
| Total variable cost per visit | $28.45 |
| Contribution margin per visit | $106.55 |
| Contribution per visit (%) | 78.9% |
| Annual fixed operating costs | $418,131 |
| Break-even visits per year | about 3,925 (327 a month) |
| Break-even revenue | $529,875 |
Funding Request and Repayment
Northbrook is asking for a $245,000 SBA 7(a) loan from Summit Community Bank.
Dr. Donovan will contribute $80,000 of her own money, bringing total startup funding to $325,000.
The loan will pay for:
- Medical and clinical equipment
- Office buildout
- Furniture and technology
- Startup licensing and credentialing
- Marketing and professional setup
- Working capital during the patient-panel and insurance payments ramp-up
The loan will run for 10 years at 11% fixed interest, which comes to about $40,499 a year. In Year 1, the startup cash reserve helps cover these payments, since the practice has not yet reached break-even.
After that, the practice can cover them from normal operations: earnings before interest, taxes, and depreciation rise to about $61,363 in Year 2 and around $136,134 in Year 3, well above the yearly loan payment.
The Quickest Way to turn a Business Idea into a Business Plan
Fill-in-the-blanks and automatic financials make it easy.


Upmetrics
Upmetrics is the #1 business planning software that helps entrepreneurs and business owners create investment-ready business plans using AI. We regularly share business planning insights on our blog. Check out the Upmetrics blog for such interesting reads. Read more
