


You might have found a good location for your urgent care clinic and worked out what equipment and staff you’ll need. But how much cash should you keep aside to cover expenses before the clinic starts bringing in enough money?
That’s a big part of planning an urgent care business. Insurance credentialing takes time, payments don’t arrive immediately, and rent and payroll still need to be covered.
To show you how to plan for this, we’ve created a sample business plan for Haverton Urgent Care, a fictional walk-in clinic in Haverton, Texas, seeking a $1 million SBA 7(a) loan.
The plan shows how Haverton handles early credentialing, staffing, startup costs, and three-year financial projections.
You can use those decisions as a reference when planning your own clinic.
Executive Summary
Haverton Urgent Care is a physician-owned walk-in clinic opening in March 2027 in Haverton, Texas, a fast-growing town in western Kaufman County about 25 miles east of downtown Dallas. Families there now drive 20 minutes to reach the nearest urgent care.
We’ll treat the illnesses and injuries that need a doctor today but not an emergency room: fevers, ear infections, sprains, cuts, and simple fractures. X-rays, lab tests, and stitches happen in the same visit.
The clinic will be open every day from 8 a.m. to 8 p.m., and local employers can send their workers to us for injury care, drug tests, and job physicals.
Our mission is to give Haverton families fast, fairly priced care for everyday illnesses and injuries, without the drive or the emergency room (ER) bill.
Owner and Team
Dr. Allison Reed, MD, owns the clinic and serves as its medical director. She is a board-certified emergency physician with 12 years in Dallas-area emergency departments, and she will work four 12-hour shifts a week.
A nurse practitioner covers the other three, with help from medical assistants, a radiology tech, and a front office team. We’ll serve young families, commuting adults, and local employers.
Patient Demand
The average U.S. urgent care center saw 33.96 patients a day in 2025. We plan for fewer: an average of 22 a day in Year 1, then 30 in Year 2 and 36 in Year 3.
Haverton’s newest neighborhoods have no other urgent care within a 15-minute drive. With an emergency physician on staff, we can also treat the broken wrists and deep cuts that other clinics send to the ER.
Revenue and Profit
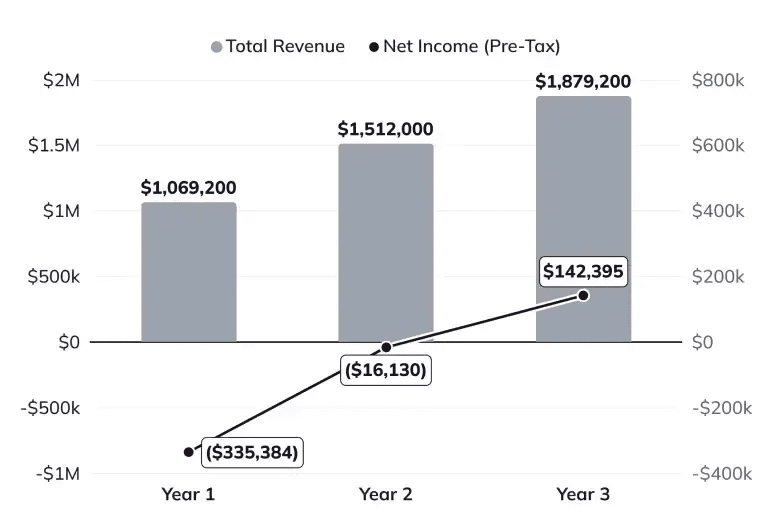
Revenue grows from $1,069,200 in Year 1 to $1,879,200 in Year 3. We expect pre-tax losses of $335,384 in Year 1 and $16,130 in Year 2, and a $142,395 profit in Year 3.
Insurance Timing
Health plans pay only after they credential the clinic and each provider, which means approving them and signing a contract. Even then, the money arrives weeks after the visit.
Dr. Reed filed with Medicare, Texas Medicaid, and six commercial plans in August 2026, seven months before opening.
Startup Loan
We’re asking Blackland Prairie Bank for a $1,000,000 SBA 7(a) loan over 10 years at a fixed 10.5% rate. Dr. Reed is putting in $300,000 of her own money, 23% of the $1,300,000 total.
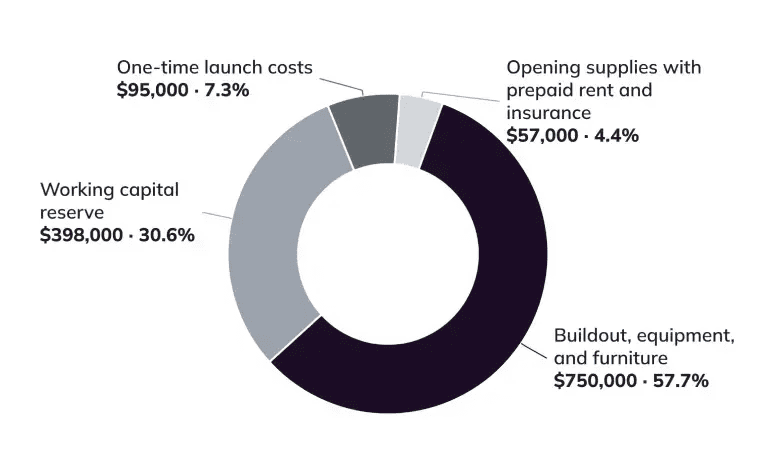
The buildout, X-ray suite, and equipment take $750,000. Another $398,000 stays in the bank as a working capital reserve for the first year, while visits build and insurance payments lag behind. The last $152,000 covers launch costs, opening supplies, and prepaid rent and insurance.
Company Overview
Haverton Urgent Care will lease a 3,000-square-foot ground-floor suite at Haverton Crossing Medical Plaza, 1850 Haverton Parkway, Suite 110, Haverton, TX 75114.
The building sits at the corner of Haverton Parkway and Prairie Wind Boulevard, next to a shopping center anchored by a grocery store and a pharmacy.
The location matters for two reasons:
- Visibility: Thousands of local drivers pass the clinic’s sign daily, helping attract walk-in patients.
- Convenience: A covered drop-off lane makes it easier for parents to bring in sick children, especially during bad weather.
Dr. Reed signed a letter of intent in July 2026 for a 10-year lease with two five-year renewal options, at a starting rent of $8,000 a month.
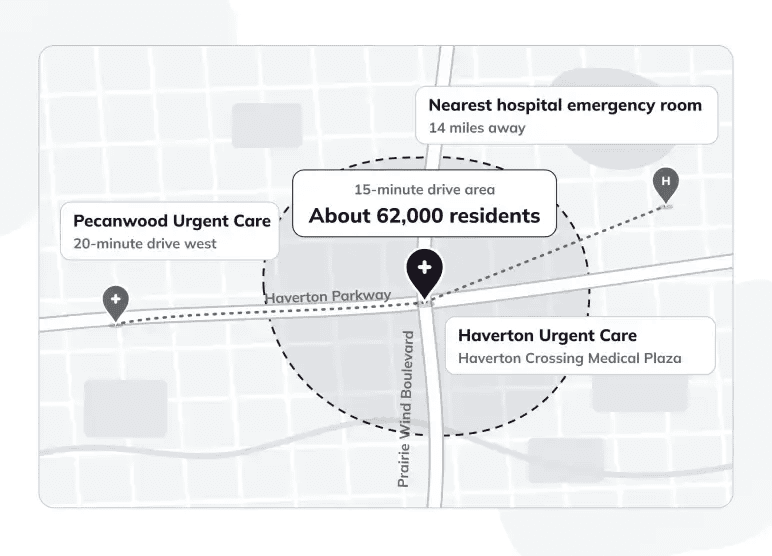
About 62,000 people live within a 15-minute drive, in Haverton and the two growing communities on either side of it. The map below shows this trade area, along with the places those residents go for care today:
Physician Owner
Dr. Reed spent the last four of her 12 years in emergency medicine as associate medical director of a suburban emergency department near Dallas.
She set up its fast-track area for minor illnesses and injuries, and waits for those patients dropped by nearly half. She is board-certified by the American Board of Emergency Medicine and has lived in Haverton with her family since 2021.
Texas doesn’t let an ordinary company employ doctors to practice medicine. Only licensed physicians can own a medical practice there.
Dr. Reed formed Haverton Urgent Care in June 2026 as a professional limited liability company (PLLC), and she owns all of it. The PLLC protects her personal assets from the clinic’s business debts. It doesn’t cover claims about her own medical care, and her malpractice policy handles those.
Long-Term Vision
We want Haverton Urgent Care to be the first place a Haverton parent thinks of when a child gets hurt at practice or spikes a fever on a Sunday.
Early Milestones
By February 2028, the end of our first year, we want to sign 20 employer accounts and keep the average visit, from check-in to discharge, under an hour. A second nurse practitioner joins in March 2028.
By the end of Year 2, we’re aiming for 150 Google reviews averaging 4.7 stars. Year 3 is when we expect to reach 36 visits a day and our first full-year profit.
Services & Prices
Haverton Urgent Care will treat common illnesses, minor injuries, and other non-emergency conditions. Patients will be able to get an exam, necessary tests, and treatment in one location whenever their condition allows.
Everyday Illness and Injury
Most patients will visit for everyday health problems such as fevers, flu, ear infections, sinus infections, urinary infections, rashes, sprains, and minor injuries.
Haverton will offer walk-in appointments seven days a week, with on-site testing and treatment for conditions that don’t require emergency care.
X-Rays, Lab Tests, and Minor Procedures
The clinic will handle many common tests and procedures on-site, so patients won’t need to visit another facility for routine diagnostics.
Services will include:
- X-rays: Chest, arm, leg, hand, foot, and spine films from $95, with a radiologist reading every image
- Lab tests: Rapid strep, flu, and COVID tests, urine and pregnancy tests, blood counts, and basic blood chemistry, $30 to $75 each
- Minor procedures: Stitches, splints, abscess drainage, and removing splinters or fishhooks, $175 to $350 on top of the visit
Other walk-in clinics often send these patients to an ER, which costs them far more.
Physicals and Vaccines
Haverton will also provide school, sports, and camp physicals, along with DOT medical examinations for commercial drivers.
Routine vaccinations, including flu shots and tetanus boosters, will be available based on the clinic’s approved services and vaccine inventory.
Employer Services
Local employers will be able to use Haverton for workplace injury care, drug and alcohol testing, pre-employment screenings, and job-related physicals.
Employers will receive a fixed price list and one monthly invoice, payable within 30 days. For workplace injuries, the clinic will provide treatment and written work-status documentation based on the patient’s medical condition.
Pricing Strategy
Haverton will accept participating insurance plans and offer published self-pay rates for patients paying without insurance.
For insured visits, the clinic will collect applicable upfront patient payments and bill the insurer for covered services. Any remaining patient balance will depend on the plan’s benefits and claim processing.
For self-pay patients, we’ll post a clear price list at the front desk and on our website so they can understand the expected cost before treatment.
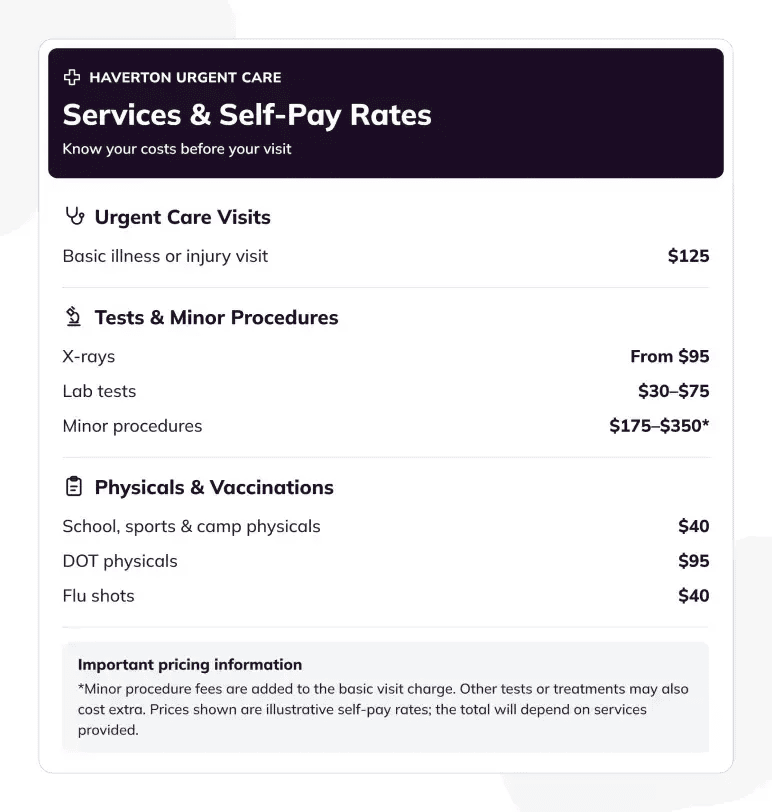
Here’s what our waiting-room price board will look like:
Employer services will be billed separately at agreed contract rates. The clinic will review its prices annually based on operating costs, insurance contracts, and local competition.
Industry and Market Analysis
Haverton is a town of new subdivisions, and most of the people moving in are young families. Their care needs follow the school year: strep and flu in winter, sports injuries in spring and fall, and a rush of physicals every August.
Kaufman County
Kaufman County is growing faster than almost anywhere in the country. The Census Bureau’s March 2026 estimates show the county had 209,235 residents on July 1, 2025, after adding 11,225 people in a single year.
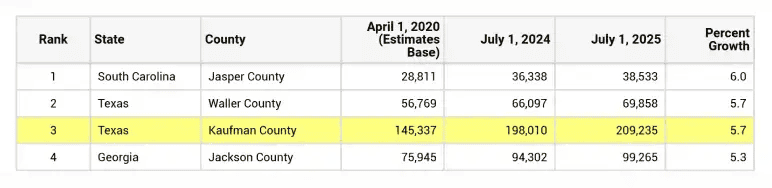
This 5.7% growth was the third-fastest of any U.S. county with 20,000 or more residents.
Most of these newcomers moved into subdivisions like Haverton’s, where shops and clinics are still catching up. Young households mean plenty of children’s visits, and parents who work until 5 or 6 need care in the evenings and on weekends, after family doctors close for the day.
We expect about one visit in ten to be self-pay. We’ll post our prices for anyone paying out of pocket.
Room for Another Clinic
As noted above, the average U.S. urgent care center saw 33.96 patients a day in 2025. At 36 a day, our Year 3 target comes to 12,960 visits a year.
If every one of those visits came from the trade area, it would work out to about one visit for every five residents each year.
In practice, around 10% of our visits will come from employers’ workers, many of whom live outside Haverton. With Pecanwood Urgent Care 20 minutes away, we expect to see most of the walk-in visits that start in Haverton.
Target Patients
Haverton will primarily serve three groups in the surrounding area:
1. Families with Children
Parents aged 25 to 45 with school-age kids make up our largest group. They come in for fevers, ear infections, and playground falls, and again each summer for school and sports physicals.
They pick a clinic by distance, insurance, and reviews, and most check in from their phones before leaving the house.
2. Working Adults and Commuters
Many Haverton residents work in Dallas or Mesquite and get home after most doctors’ offices have closed. They need evening and weekend care for sinus infections, back pain, and minor injuries, and they won’t sit in a waiting room for two hours.
3. Local Employers
Warehouses, contractors, school districts, and auto shops within 20 minutes of the clinic need a place to send injured workers and new hires. Their supervisors care about one thing above all: a clear answer, the same day, on when the worker can come back.
Recent Trends
A few changes in walk-in care shape how we’ll run the clinic:
- Families now bring many problems to urgent care that once meant a long night in the ER.
- Patients expect to save their spot online and wait at home.
- Higher deductibles push patients to compare prices before they choose a clinic.
- North Texas has many freestanding ERs, and patients often confuse them with urgent care until the bill arrives.
Competitive Analysis
A Haverton parent with a sick child at 6 p.m. has six real choices, and only one of them is another urgent care. Each one works for some patients and falls short for others:
| Competitors | Hours | X-Ray on Site | Strengths | Weaknesses |
|---|---|---|---|---|
| Pecanwood Urgent Care, 20 minutes west | 8 a.m. – 8 p.m. daily | Yes | Nine years in the area, strong reviews, eight exam rooms, and two providers on busy evenings | The drive, evening waits that often run past an hour, and no program for employers |
| Freestanding emergency rooms, two within 15 minutes | 24 hours | Yes, plus CT | Short waits and ER equipment close to home | ER prices and facility fees, and some are out of network |
| Hospital emergency room, 14 miles away | 24 hours | Yes, plus CT | Treats anything, day or night | Long waits for minor problems and the highest bills |
| Retail pharmacy clinics | Mostly daytime | No | Low prices for simple problems like pink eye | No X-rays, stitches, or splints |
| Family doctors’ offices | Weekdays | Rarely | Know the patient’s history | Few same-day sick visits and no evening hours |
| Telehealth visits | 24 hours | No | Cheap and quick from home | Can’t examine, test, or treat an injury |
Pecanwood and the freestanding ERs give us the most competition. Pecanwood has a loyal following and more rooms than we do, and the freestanding ERs never close.
Competitive Advantage
For most of Haverton, we will simply be closer, and parents with a sick child go to the nearest clinic they trust. We will also be in-network with the major health plans on opening day and able to finish most visits in one stop, X-ray and lab results included.
The bigger difference is Dr. Reed’s training. An emergency physician can set a simple fracture, close a deep cut, or drain an abscess that many urgent cares send on to the ER. Patients get that care at urgent care prices, and we post those prices on the wall and on our website.
Insurance Credentialing & Billing
Getting into insurance networks is the most important step before we open. Commercial health plans will pay for six in ten of our visits, and none of them pays a clinic without a contract.
Payer Mix
In Year 1, an average visit will bring in $135 once every payer has paid. Here’s who pays for our visits, and how much each pays on average:
| Payer | Share of Visits (Year 1) | Average Net Payment per Visit |
|---|---|---|
| Commercial health plans | 60% | $150 |
| Medicare and Medicare Advantage | 12% | $115 |
| Texas Medicaid and CHIP plans | 8% | $80 |
| Self-pay patients | 10% | $120 |
| Employer accounts | 10% | $128 |
| Blended average | 100% | $135 |
The average climbs to $140 in Year 2 and $145 in Year 3, with small yearly increases in our commercial contracts and more visits that include an X-ray or a procedure.
Credentialing Timeline
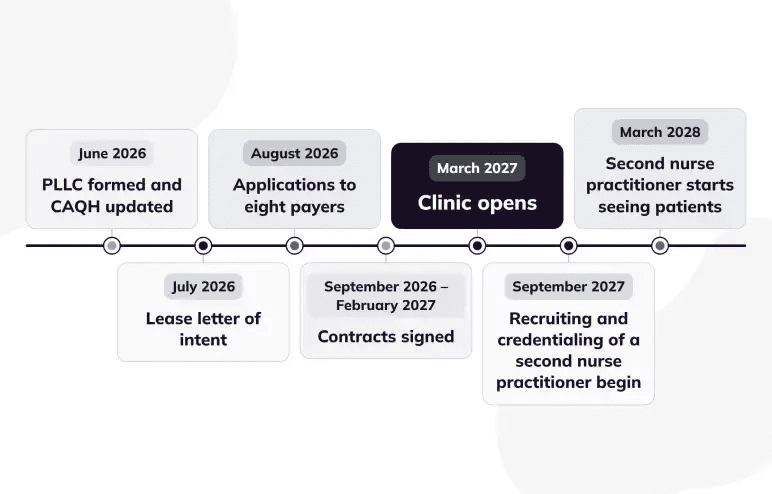
Dr. Reed formed the PLLC in June 2026, got the clinic’s group NPI number, and updated her CAQH profile, the shared record most commercial plans use to check a provider’s background.
In July, she signed the letter of intent for the suite, because each health plan needs the clinic’s service address before it will process anything.
The applications went out together in August 2026, to eight payers:
- Medicare, through Novitas Solutions, the Medicare contractor for Texas
- Texas Medicaid, through TMHP
- Six commercial plans: Blue Cross and Blue Shield of Texas, UnitedHealthcare, Aetna, Cigna, Humana, and Wellpoint
From September through February, the administrator follows up with each plan every week and logs every contract as it comes back.
We add our nurse practitioner to each application as soon as she signs her offer. We’ve allowed up to 180 days for the slowest plans, which still leaves a month before we open in March 2027. The timeline below shows the full sequence, through the second nurse practitioner’s first shift:
Why We Wait for Contracts
Medicare will pay a new practice for visits from up to 30 days before its enrollment takes effect. Most commercial plans won’t backdate anything, and they treat any visit before the contract date as out of network.
Opening early would mean advertising to patients who then can’t use their insurance with us. If one plan is still missing on opening day, the front desk will tell its members at check-in and offer our self-pay price.
The same goes for each new provider: every plan must credential them before we can bill for their visits. Credentialing for our second nurse practitioner starts about six months before her first shift.
Cash Timing
On average, insurers will pay us about 40 days after a visit.
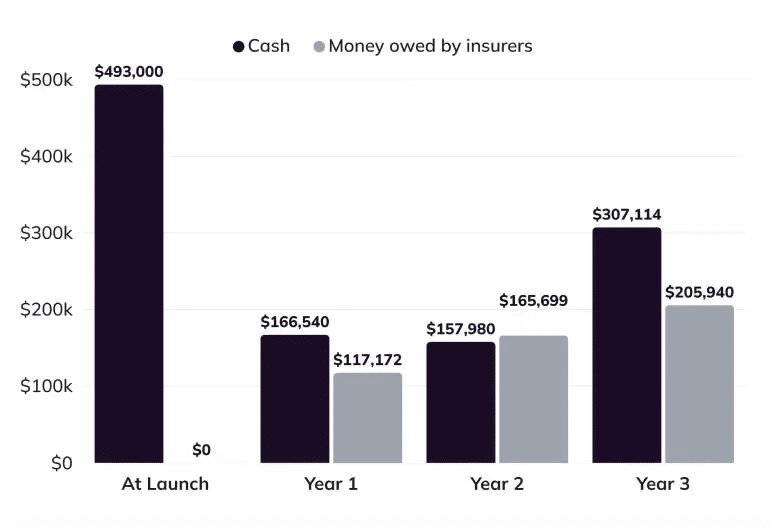
Rent, payroll, and loan payments are due every month regardless, and the amount we’re owed keeps growing as visits grow. By the end of Year 1, insurers will owe us $117,172 for care we’ve already given.
That money sitting in unpaid claims, plus a full year of fixed costs while visits are still building, explains the Year 1 loss. We seized the $398,000 reserve to cover both.
Billing
Tallgrass Revenue Partners, an urgent care billing company in Dallas, will submit our claims, post payments, and work our denied claims for about 4% of what we collect.
The front desk checks coverage and collects copays, and providers close their charts before the end of each shift. Claims go out within two days.
Each Monday, the administrator reviews unpaid claims, denials, and how long each insurer is taking to pay. This lets us spot a slow-paying plan within a month.
Marketing & Sales Strategy
People look for urgent care in a hurry, usually on a phone, and usually after checking whether a clinic takes their insurance. We want to be the first name they see and to appear in their plan’s directory when they look.
Opening Plans
The $35,000 launch budget covers our brand design, a website with online check-in, a lighted sign facing Haverton Parkway, and opening events.
A month before opening, we’ll set up our Google Business Profile and confirm our listing in every insurer’s provider directory.
The last two weeks before opening are for meeting neighbors in person:
- Dr. Reed speaks at two PTA meetings.
- We hold an open house with free blood pressure checks.
- The administrator visits the 40 largest employers within 20 minutes of the clinic.
Sports physicals cost $25 for the first month.
Marketing Channels
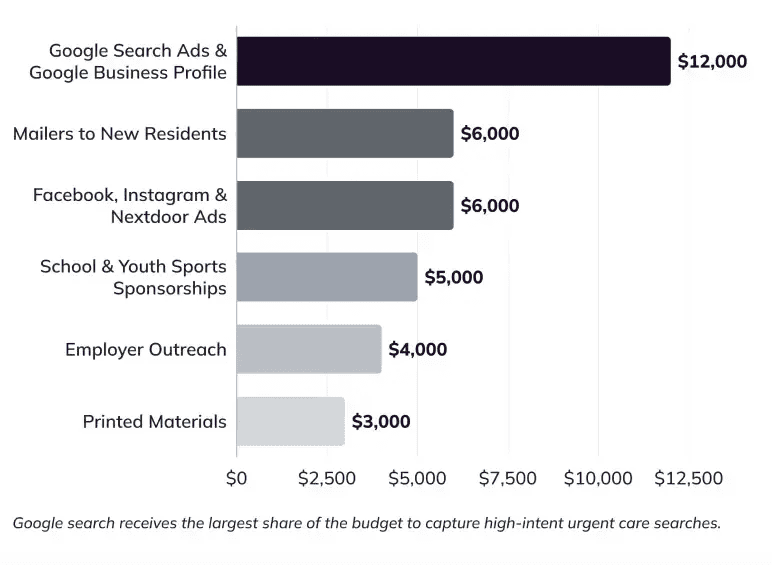
Ongoing marketing runs $36,000 in Year 1 and drops to $30,000 a year afterward, once reviews and repeat patients bring in more of our new visits.
Here’s where the Year 1 money goes:
Repeat Visits
The day after a visit, each patient gets a text asking how they’re feeling, with a link to leave a review. Anyone who had stitches or a splint gets a reminder about their follow-up. In September, past patients hear from us when flu shots arrive.
Once a month, the administrator checks where new patients heard about us, the average visit time, and the review count. We then shift spending toward the channels that bring patients back.
Operations & Staffing
The clinic is open from 8 a.m. to 8 p.m. every day except New Year’s Day, Easter Sunday, July 4, Thanksgiving Day, and Christmas Day, or 360 days a year.
Most visits take under an hour from check-in to discharge, because providers order X-rays and lab tests at the start of the exam. If a patient shows signs of a heart attack or stroke, we call an ambulance right away.
Weekly Schedule
We expect Mondays and weekends to be our busiest days, along with weekday evenings after work and school. We’ve set up the week around them:
| Coverage Period | Staff Assigned | Main Focus |
|---|---|---|
| Monday & Tuesday | Dr. Reed, medical assistant, front desk | Patient care and early-week demand |
| Wednesday–Friday | Nurse practitioner, medical assistant, front desk | Routine and after-work visits |
| Weekday afternoons & evenings | Radiology technician (additional coverage) | X-rays and lab support |
| Saturday & Sunday | Dr. Reed, medical assistant, front desk | Weekend walk-in visits |
Our medical assistants hold limited X-ray certificates and take routine films when the tech is off. Mornings are quieter, and the team uses them to restock rooms, run lab quality checks, and call patients with test results.
Facility & Equipment
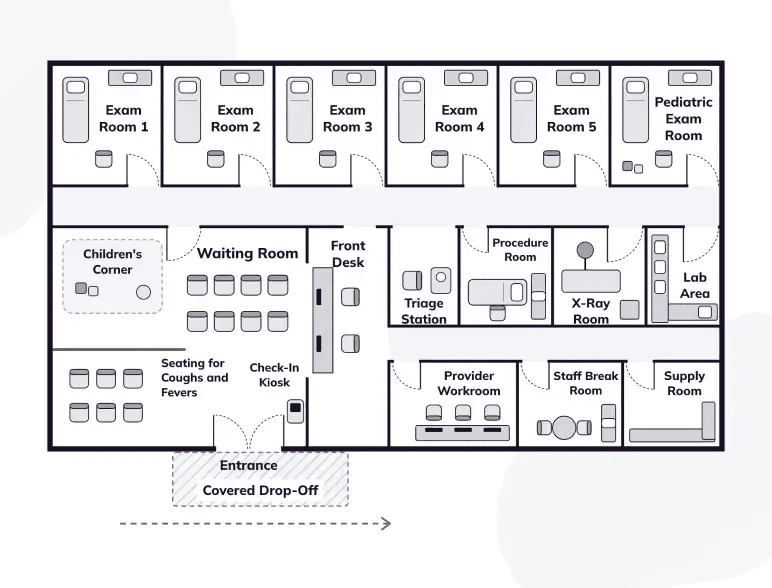
The suite has six exam rooms, one of them set up for children, plus a procedure room for stitches and splints.
The X-ray room uses a digital system, so images are on screen in seconds, and the lab area holds blood count, chemistry, and urine analyzers. Service contracts on the X-ray system and analyzers cover repairs and yearly calibration.
The floor plan below shows how we’ve arranged the suite, with separate seating up front for patients with coughs and fevers:
Vendors & Partners
We rely on a few outside partners to keep the clinic running:
- Experity: Our urgent care health record and practice-management system, with online check-in, for about $2,500 a month
- Tallgrass Revenue Partners: Our billing company in Dallas
- Corvallen Radiology Associates: A Dallas radiology group that reads every X-ray within a few hours and bills insurers for its own read
- Labcorp: Picks up the tests we don’t run in-house each evening and bills the patient’s insurer directly
- McKesson Medical-Surgical: Delivers medical supplies, vaccines, and lab test kits the next day
- A TCEQ-registered medical waste hauler: Collects sharps and biohazard waste every two weeks
Licenses & Approvals
Texas has no facility license for urgent care clinics. The clinic, its providers, its X-ray machine, and its lab each need their own approvals instead:
| Approval | Issued By | Timing and Cost |
|---|---|---|
| PLLC certificate of formation (Form 205) | Texas Secretary of State | Filed June 2026, $300 |
| Physician license | Texas Medical Board | Renewed every two years |
| Nurse practitioner license and prescriptive authority agreement | Texas Board of Nursing, with Dr. Reed as delegating physician | Quality meetings at least once a month |
| X-ray certificate of registration | Texas Department of State Health Services, Radiation Control | $600 every two years, with Dr. Reed as radiation safety officer |
| X-ray operator certificates (MRT and LMRT) | Texas Medical Board | $130 for each LMRT |
| CLIA Certificate of Compliance | Centers for Medicare & Medicaid Services, through Texas Health and Human Services | Valid for two years; we test under a registration certificate until the state survey |
| DEA registration for each prescriber | Drug Enforcement Administration | Renewed every three years |
| Certificate of occupancy | City of Haverton | After the buildout passes inspection |
| Unemployment tax account and franchise tax report | Texas Workforce Commission and Texas Comptroller | Before the first payroll, then yearly |
Texas no longer requires a separate state registration for controlled substances, so the DEA registration is the only one we need.
We’ll also keep an OSHA bloodborne pathogens plan and HIPAA privacy and security policies, and carry malpractice, general liability, property, and workers’ compensation insurance.
Texas rules don’t allow an unlicensed clinic to use “emergency” or “ER” in its name or ads. Our signs will read “Urgent Care — Not an Emergency Room.”
Staffing and Compensation
Dr. Reed takes a $180,000 salary in Year 1 as owner and medical director.
Beyond her four clinical shifts, she leads clinical quality, signs the prescriptive authority agreement that lets our nurse practitioner prescribe, and manages payer relationships and the loan.
Haverton will have the following clinical and administrative staff to support daily operations:
| Position | Staffing | Key Responsibilities | Annual Salary |
|---|---|---|---|
| Nurse Practitioner | 1 (three 12-hour shifts/week) | Patient exams, diagnosis, and treatment | $128,000 |
| Medical Assistants | 2 | Triage, patient rooming, lab tests, and permitted X-rays | $80,000 |
| Radiology & Lab Technician | 1 | X-rays, lab testing, and equipment checks | $60,000 |
| PRN Clinical Staff | As needed | Vacation, sick-day, and holiday coverage | $9,992 |
| Practice Administrator | 1 | Scheduling, payroll, purchasing, billing follow-up, and employer accounts | $68,000 |
| Front Desk Staff | 2 | Patient check-in, insurance verification, copays, and calls | $73,000 |
| Total | $418,992 |
This brings clinical pay to $277,992 and front office pay to $141,000 in Year 1.
Adding a Second Provider
A second nurse practitioner is our biggest cost decision after opening. Recruiting starts when daily visits average 26 or more for four weeks in a row, or when evening waits pass 45 minutes on most days.
We expect that point around September 2027. With about six months for credentialing, she would start seeing patients in March 2028, at the beginning of Year 2, and cover the afternoon and evening shift and the busiest weekend days. A third medical assistant and a part-time front desk person follow in Year 3.
Financial Plan
The forecast starts from visits a day and the average payment per visit. Year 1 loses money because a full year of fixed costs and $95,000 of launch costs arrive before visits reach their full level, and the clinic turns its first profit in Year 3.
Startup Costs
| Category | Amount |
|---|---|
| Clinic buildout | $260,000 |
| Medical and diagnostic equipment | $180,000 |
| X-ray suite | $150,000 |
| Lab equipment | $60,000 |
| Furniture and fixtures | $55,000 |
| Computers and IT equipment | $45,000 |
| Opening medical supplies | $12,000 |
| Lease deposit and prepaid rent | $24,000 |
| Prepaid insurance | $21,000 |
| Launch marketing | $35,000 |
| Licenses, permits, and inspections | $20,000 |
| Legal, professional, and credentialing setup | $40,000 |
| Working capital reserve | $398,000 |
| Total Startup Costs | $1,300,000 |
Financial Assumptions
| Assumption | Year 1 | Year 2 | Year 3 |
|---|---|---|---|
| Operating days | 360 | 360 | 360 |
| Average visits per day | 22 | 30 | 36 |
| Patient visits | 7,920 | 10,800 | 12,960 |
| Average net revenue per visit | $135 | $140 | $145 |
| Medical supplies (share of revenue) | 12% | 12% | 12% |
| Clinical staff pay (share of revenue) | 26% | 26% | 26% |
| Payroll tax rate | 7.65% | 7.65% | 7.65% |
| Days to collect from insurers | 40 | 40 | 40 |
| Days to pay suppliers | 30 | 30 | 30 |
| Medical supplies on hand (days) | 30 | 30 | 30 |
| Loan interest rate (fixed, 10 years) | 10.5% | 10.5% | 10.5% |
| Loan payments per year | $161,964 | $161,964 | $161,964 |
Projected Profit & Loss
| Category | Year 1 | Year 2 | Year 3 |
|---|---|---|---|
| Revenue | |||
| Total Revenue | $1,069,200 | $1,512,000 | $1,879,200 |
| Direct Costs | |||
| Medical supplies | $128,304 | $181,440 | $225,504 |
| Clinical staff pay | $277,992 | $393,120 | $488,592 |
| Payroll taxes on clinical pay | $21,267 | $30,074 | $37,377 |
| Total Direct Costs | $427,563 | $604,634 | $751,473 |
| Gross Profit | $641,637 | $907,366 | $1,127,727 |
| Gross Margin | 60.0% | 60.0% | 60.0% |
| Operating Expenses | |||
| Owner and medical director salary | $180,000 | $200,000 | $220,000 |
| Administrative and front desk salaries | $141,000 | $148,000 | $170,000 |
| Payroll taxes on salaries | $24,557 | $26,622 | $29,835 |
| Rent | $96,000 | $98,000 | $100,000 |
| Insurance | $42,000 | $44,000 | $46,000 |
| Billing and collections | $43,000 | $60,000 | $75,000 |
| Health record and practice software | $30,000 | $31,000 | $32,000 |
| Phone, utilities, and internet | $24,000 | $25,000 | $26,000 |
| Marketing | $36,000 | $30,000 | $30,000 |
| Office, cleaning, and medical waste | $18,000 | $19,000 | $20,000 |
| Accounting and legal | $18,000 | $18,000 | $19,000 |
| Equipment service contracts | $15,000 | $16,000 | $17,000 |
| Launch marketing (one-time) | $35,000 | $0 | $0 |
| Licenses and permits (one-time) | $20,000 | $0 | $0 |
| Professional and credentialing setup (one-time) | $40,000 | $0 | $0 |
| Total Operating Expenses | $762,557 | $715,622 | $784,835 |
| EBITDA | ($120,920) | $191,744 | $342,892 |
| Depreciation | $112,286 | $112,286 | $112,286 |
| EBIT | ($233,206) | $79,458 | $230,606 |
| Interest Expense | $102,178 | $95,588 | $88,211 |
| Net Income (Pre-Tax) | ($335,384) | ($16,130) | $142,395 |
Projected Cash Flow
| Category | Year 1 | Year 2 | Year 3 |
|---|---|---|---|
| Beginning Cash | $493,000 | $166,540 | $157,980 |
| Operating Activities | |||
| Net income (pre-tax) | ($335,384) | ($16,130) | $142,395 |
| Depreciation | $112,286 | $112,286 | $112,286 |
| Change in accounts receivable | ($117,172) | ($48,527) | ($40,241) |
| Change in medical supplies | $1,454 | ($4,367) | ($3,622) |
| Change in accounts payable | $35,142 | $14,554 | $12,069 |
| Change in prepaid expenses | $37,000 | $0 | $0 |
| Net Cash from Operations | ($266,674) | $57,816 | $222,887 |
| Financing Activities | |||
| Loan principal repayment | ($59,786) | ($66,376) | ($73,753) |
| Net Cash from Financing | ($59,786) | ($66,376) | ($73,753) |
| Net Change in Cash | ($326,460) | ($8,560) | $149,134 |
| Ending Cash | $166,540 | $157,980 | $307,114 |
Projected Balance Sheet
| Category | At Launch | Year 1 | Year 2 | Year 3 |
|---|---|---|---|---|
| Assets | ||||
| Cash | $493,000 | $166,540 | $157,980 | $307,114 |
| Accounts receivable | $0 | $117,172 | $165,699 | $205,940 |
| Medical supplies | $12,000 | $10,546 | $14,913 | $18,535 |
| Prepaid expenses and deposits | $45,000 | $8,000 | $8,000 | $8,000 |
| Equipment and buildout (net) | $750,000 | $637,714 | $525,428 | $413,142 |
| Total Assets | $1,300,000 | $939,972 | $872,020 | $952,731 |
| Liabilities | ||||
| Accounts payable | $0 | $35,142 | $49,696 | $61,765 |
| SBA loan | $1,000,000 | $940,214 | $873,838 | $800,085 |
| Total Liabilities | $1,000,000 | $975,356 | $923,534 | $861,850 |
| Equity | ||||
| Owner capital | $300,000 | $300,000 | $300,000 | $300,000 |
| Retained earnings | $0 | ($335,384) | ($351,514) | ($209,119) |
| Total Equity | $300,000 | ($35,384) | ($51,514) | $90,881 |
| Total Liabilities & Equity | $1,300,000 | $939,972 | $872,020 | $952,731 |
Break-Even Analysis
| Metric | Value |
|---|---|
| Average net revenue per visit (Year 2) | $140.00 |
| Variable cost per visit (supplies, clinical pay, and payroll taxes) | $56.00 |
| Contribution per visit | $84.00 |
| Fixed operating costs (Year 2) | $715,622 |
| Break-even visits per year (before depreciation and interest) | 8,519 |
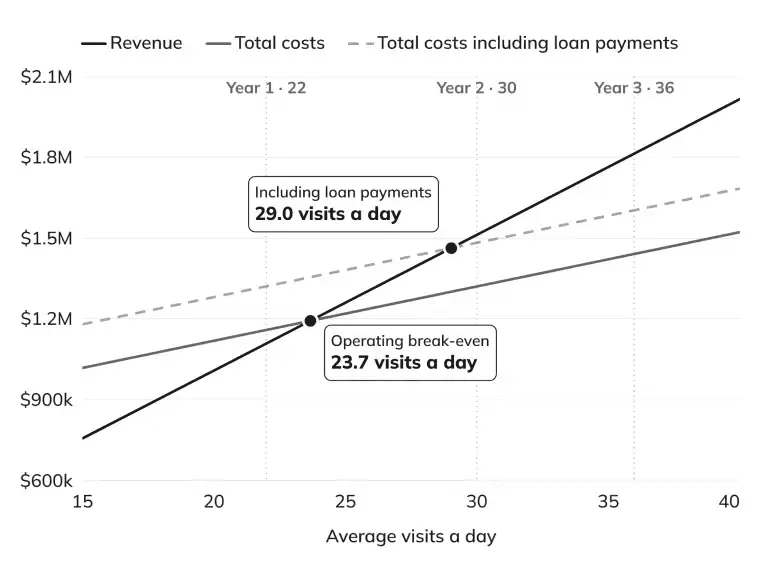
| Break-even visits per day (before depreciation and interest) | 23.7 |
| Break-even visits per day (including loan payments) | 29.0 |
| Forecast visits per day (Year 2) | 30 |
Funding Request
Haverton Urgent Care is requesting a $1,000,000 SBA 7(a) loan from Blackland Prairie Bank, repaid over 10 years at $13,497 a month, or $161,964 a year. Dr. Reed’s $300,000 cash investment covers the rest of the $1,300,000 budget. She will personally guarantee the loan, and the clinic’s equipment, X-ray suite, and buildout will secure it.
| Source | Amount |
|---|---|
| SBA 7(a) loan (Lone Star Community Bank) | $1,000,000 |
| Owner equity contribution (Dr. Allison Reed) | $300,000 |
| Total Startup Capital | $1,300,000 |
Year 1 EBITDA is a loss of $120,920, and the first year’s loan payments come out of the reserve.
In Year 2, EBITDA covers the payments 1.18 times, short of the 1.25 times many lenders look for, and in Year 3 it covers them 2.12 times. The lowest year-end cash balance is $157,980, at the end of Year 2.
Owner’s equity dips below zero in Years 1 and 2 because of the early losses, then turns positive at $90,881 in Year 3. By then, the loan balance is down to $800,085.
Risk Analysis
A new clinic faces most of its risk in the first 18 months. These are the risks we watch most closely, and how we plan to handle each one:
(1) Slow credentialing
If a major plan isn’t active by March 2027, we’ll offer its members our self-pay prices. If two or more large plans run late, we’ll push opening back by up to a month.
(2) Slow visit growth
Each visit a day below plan costs us about $30,000 a year in contribution. We’ll sign employer accounts first, since they bring steady weekday visits, and wait on the second NP until we meet our hiring rule.
(3) Lower insurance payments
A Medicare cut or a tough commercial renewal would lower our average payment. We spread visits across eight payers and our employer accounts, and we review each contract a year before it renews.
(4) Dr. Reed can’t work
She covers four of our seven weekly shifts. Two emergency physicians from her former group can cover shifts on short notice, and she carries disability insurance from opening day.
(5) A slow first summer
Urgent care runs busiest from December to March, and we open in March. We’ll promote back-to-school physicals in July and August and plan our cash around the dip.
(6) Staff turnover
Medical assistants with X-ray certificates are hard to replace. We’ll pay for LMRT training for promising assistants and keep a list of trained PRN staff.
The Quickest Way to turn a Business Idea into a Business Plan
Fill-in-the-blanks and automatic financials make it easy.


Upmetrics
Upmetrics is the #1 business planning software that helps entrepreneurs and business owners create investment-ready business plans using AI. We regularly share business planning insights on our blog. Check out the Upmetrics blog for such interesting reads. Read more
